Why Constipation Makes Bladder Leaks Worse — the Link Nobody Mentions
Quick Answer: A full rectum sits directly behind the bladder and physically reduces its capacity, while repeated straining stretches and weakens the same pelvic floor you are trying to strengthen. Constipation is a recognised risk factor for urinary incontinence, and in many people addressing it produces more improvement than adding more pelvic floor exercises.
This is general information, not medical advice.


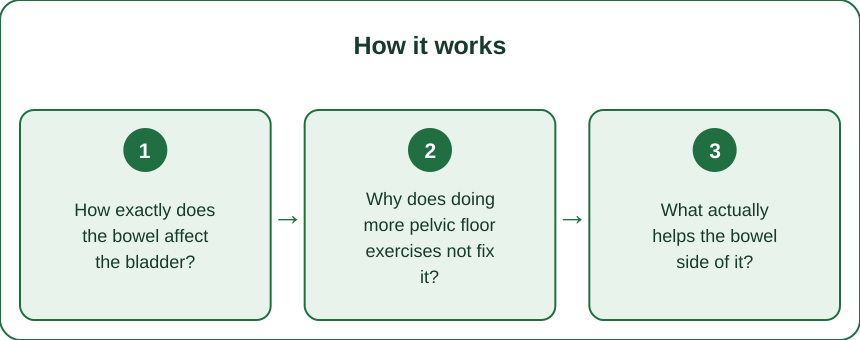
How exactly does the bowel affect the bladder?
They share a very small space. The rectum sits immediately behind the bladder in the pelvis. When it is loaded, it presses forward and reduces how much the bladder can comfortably hold, which produces urgency and more frequent trips.
Straining is the bigger problem. Bearing down repeatedly pushes the pelvic organs downward and stretches the pelvic floor and the nerves that supply it. Doing that daily for years is a well-documented contributor to pelvic floor dysfunction and prolapse.
They share nerve supply. The same sacral nerve roots supply the bladder and the bowel, so irritation or dysfunction in one commonly shows up in the other.
A loaded bowel also changes how you brace. Discomfort in the abdomen alters how you hold your trunk during lifting, coughing and exercise, and that changes pressure distribution in the pelvis.
And the pelvic floor has to relax to empty either one. A pelvic floor that has learned to stay tight — which is surprisingly common in people doing lots of squeezing exercises — makes both bladder and bowel emptying harder, which is where the cycle becomes self-reinforcing.
Why does doing more pelvic floor exercises not fix it?
Because the exercises are addressing one part of a system. If your pelvic floor is being stretched by daily straining, adding squeezes without stopping the straining is filling a bath with the plug out.
Some pelvic floors are too tight rather than too weak. An overactive pelvic floor produces leaking, urgency and difficulty emptying, and squeezing exercises make it worse. This is one of the most common reasons a diligent programme does nothing.
Technique degrades without feedback. A substantial proportion of people doing pelvic floor exercises from written instructions are doing them incorrectly, often bearing down rather than lifting, which is actively counterproductive.
And there are usually several contributors. Constipation, chronic cough, heavy lifting technique, body weight, hormonal changes and childbirth history all stack, so addressing one in isolation often produces modest results.
Which is why assessment matters. A pelvic health physiotherapist can tell you within one appointment whether your floor is weak, tight, or poorly coordinated, and those three need genuinely different treatment.

What actually helps the bowel side of it?
Fibre, gradually. Aim to increase toward roughly 30 grams a day, adding slowly over a few weeks rather than all at once, since a sudden jump produces bloating and can make things temporarily worse.
Fluid alongside fibre, not instead of it. Fibre without adequate fluid makes constipation worse. The two work as a pair.
Change the position. A footstool that raises the knees above the hips straightens the anorectal angle and reduces the need to strain substantially. It is a cheap and genuinely effective intervention.
Do not hold on. Responding to the urge when it arrives, rather than deferring it, keeps the whole system working. Deferring repeatedly is one of the most common causes of the problem.
Use the gastrocolic reflex. Bowel activity increases after eating, particularly after breakfast, so allowing time in the morning works with your physiology instead of against it.
Movement helps directly. Regular walking improves gut transit time measurably, and it is one of the few interventions that helps both the bowel and the pelvic floor at once.
And breathe out on exertion. Exhaling while you exert rather than holding your breath applies to lifting, coughing and the toilet alike — it keeps downward pressure off the pelvic floor.
What Nobody Tells You About the Bowel-Bladder Connection
This is standard practice in pelvic health and almost unknown outside it. Any pelvic floor physiotherapist will ask about your bowels in the first appointment, and most people are surprised by the question.
Children’s continence services have known this for decades. Treating constipation is one of the first-line interventions for childhood bedwetting, with good evidence, and the same mechanism applies in adults.
Iron supplements are a common hidden cause. Many women take iron for heavy periods or low ferritin, constipation is a frequent side effect, and the connection to worsening leaks is almost never made.
So are several other common medications. Some painkillers, antidepressants, antihistamines and blood pressure medications all slow the bowel, and reviewing them is worth doing before adding anything new.
Autumn and winter make it worse for a lot of people. Less fluid intake in cool weather, less walking, and more heavy food all push in the same direction, which is why symptoms that were stable in summer sometimes deteriorate in October.
Straining also affects the anal sphincter, and long-standing constipation is associated with bowel control problems as well as bladder ones. It is worth addressing early rather than living with it.
And the improvement can be quick. Where constipation is a significant contributor, people frequently notice a difference in bladder symptoms within a few weeks of resolving it, which is faster than pelvic floor strengthening alone typically produces.
FAQ: Bowel and Bladder Questions, Answered
How do I know if I am actually constipated?
It is about difficulty and completeness, not just frequency. Straining, hard stools, a feeling of incomplete emptying, or needing to strain more than occasionally all count even if you go every day.
Should I take a laxative?
Speak to a pharmacist or doctor rather than self-treating long term. Different types work in different ways, and the right one depends on the cause. Fibre, fluid and position come first.
Will fixing this alone stop my leaks?
Sometimes, and often it is one of several factors. It is worth doing regardless because straining actively works against everything else you are trying to do.
When should I see someone about it?
Any change in bowel habit lasting more than a few weeks, blood, unexplained weight loss or significant pain needs medical assessment promptly rather than dietary experimentation.
TL;DR:
- A loaded rectum physically reduces bladder capacity, and straining stretches the pelvic floor you are trying to strengthen.
- If squeezing exercises are not working, your floor may be too tight rather than too weak — get assessed.
- Build fibre toward 30g gradually with fluid, use a footstool, and never defer the urge.
- Check iron supplements and other medications as hidden causes.
- Exhale on exertion — lifting, coughing and the toilet alike.
The leaks may not be a bladder problem at all.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
